

Light gray square, with a dark gray border on the sides.

Blog

Walk Into the Room With a Plan You'd Defend

September 29, 2026

Part 1 of 6 in Circle CVI's Structural Heart series. Every Scan. One Plan. One Platform.


The annulus measurement decides the case.


Valve choice follows from it. So does sizing, so does the degree of oversizing, so does whether the root tolerates that oversizing, and so does whether you spend the end of an otherwise clean case managing a paravalvular leak. By the time the patient is on the table, that measurement was made days earlier, in a post-processing application the operator may never open, by a reader whose work arrives as a number on a report.


For a procedure this dependent on millimeters, that is worth examining.

The measurement varies more than most operators assume


Not between good readers and bad ones. Between a good reader and the same good reader, on the same scan, on a different day.


In a study of 82 TAVR screening CTAs read twice by each of three readers, a single reader arrived at a different device-size category between their own repeated measurements in 22 to 26 percent of cases. Moving to a multi-reader strategy cut that to 5 to 10 percent. The study was single-center and the readers spanned a radiologist, a 3D-lab technologist and a medical student, but the direction is the point: annulus measurement carries more internal variance than a single number on a report suggests.


Software adds its own. Comparing two established planning packages across 100 patients, mean annulus area came out at 482 mm² on one and 464 mm² on the other, with the difference significant at p < 0.001. Perimeter and coronary heights diverged the same way. Had the fully automated output been accepted without correction, prosthesis size would have changed in 18 percent of patients. Manual correction of the automated contours brought that down to 4 percent.


Two readers, two packages, two answers. The operator inherits one of them.


What sizing error actually costs


The relationship between oversizing and paravalvular regurgitation is not theoretical. In 835 intermediate-risk patients receiving a balloon-expandable valve, degree of oversizing tracked inversely with the frequency and severity of paravalvular regurgitation, with area and perimeter oversizing performing equally as predictors at an AUC of 0.78.


Push oversizing too far in the wrong anatomy and the consequence changes character. The landmark analysis of aortic root rupture during balloon-expandable TAVR identified moderate-to-severe subannular calcification and prosthesis oversizing at or above 20 percent as the anatomic and procedural features associated with rupture.


At the other end, undersizing has its own bill. Across 10,298 TAVR patients at 21 international centers, 1.0 percent required urgent implantation of a supplementary valve, driven principally by residual aortic regurgitation and valve malposition. Device success in those patients was 70.4 percent against 92.2 percent, and 30-day mortality was 11.8 percent against 5.5 percent.


One percent is a small number until it is your case.


Why CT carries the measurement


This is settled, and has been for some time. The SCCT expert consensus on CT imaging for TAVR remains the reference document for acquisition, annulus and LVOT measurement, fluoroscopic angulation reporting, and vascular access assessment. The European Society of Cardiovascular Radiology consensus standardizes the same ground and proposes a reporting template for it. The EACVI Task Force consensus on interventional cardiovascular imaging assigns annulus and aortic root measurement to CT alongside 3D transesophageal echo, and requires that pre-procedural assessment establish annular size and shape along with the extent and distribution of calcification.


The outcome evidence supports the practice. A meta-analysis of six studies comparing CT-based against echo-based annulus sizing found moderate-or-greater paravalvular regurgitation substantially less common with CT-based sizing than with 2D TEE, at an odds ratio of 0.31, with no difference in annular rupture or 30-day mortality between modalities. CT reduces leak. It has not been shown to reduce death, and the honest version of the claim stops there.


What automation should do, and what it should not


The published evidence on automated annulus and landmark detection is real and still maturing. The largest study to date trained on 1,252 pre-TAVR CT scans and validated externally across 19 hospitals, reporting intraclass correlation up to 0.998 for measurement and accuracy up to 0.989 for detection of anatomical risk factors. It is retrospective, and the external cohort was 100 patients. A 2024 review of AI in TAVR imaging is blunt that the field is constrained by small cohorts, limited scope and variable performance, and that rigorous validation remains outstanding.


Which is the correct way to think about it. The value of assisted detection is not that it removes the operator's judgment from the measurement. It is that it removes the part of the work where fatigue and repetition introduce variance, and leaves the judgment where it belongs.


In cvi42, assisted annulus and landmark detection in the Interventional Planning Suite covering aortic, mitral and LAAC planning removes 80 to 100 clicks from a typical case by Circle's own measurement. Every contour it proposes is physician-editable. The analysis runs on-premises, so patient data stays inside the institution. And the 18-percent-to-4-percent finding above is the argument for exactly this design: automation that proposes and a clinician who disposes produces better agreement than either alone.


The volume argument is no longer hypothetical


EARLY TAVR randomized 901 patients with asymptomatic severe aortic stenosis and preserved ejection fraction to TAVR or clinical surveillance across 75 sites. The primary composite of death, stroke or unplanned cardiovascular hospitalization occurred in 26.8 percent of the TAVR arm against 45.3 percent under surveillance, a hazard ratio of 0.50. Read it precisely: the composite was driven by unplanned hospitalization, at 20.9 percent against 41.7 percent. Death and stroke individually did not differ significantly. What the trial establishes is not a mortality case for early intervention but that 87 percent of the surveillance arm crossed over to valve replacement anyway.


Guidelines have started to move. The 2025 ESC/EACTS valvular heart disease guidelines lowered the age at which TAVI carries a Class I, Level A recommendation to 70 in patients with suitable anatomy for transfemoral access, and now state that intervention should be considered in asymptomatic patients with preserved ejection fraction at Class IIa, Level A. In the United States, CMS finalized a revised TAVR national coverage determination on 10 September 2026, extending coverage to asymptomatic severe aortic stenosis under coverage with evidence development and removing the CED requirement for symptomatic patients entirely.


Referral volume grows from here. The constraint moves from procedure capacity to evaluation capacity, and evaluation capacity is a CT and a heart-team decision.


The scans that come after


The index procedure is not the last time that anatomy needs reading.


The 2025 multi-society consensus on CT for prosthetic heart valve assessment is careful about this: cardiac CT is not used for routine screening of valve degeneration. It is indication-driven, and the indications are real. Suspected leaflet thrombosis is one, and hypoattenuated leaflet thickening is common enough to matter, rising from 10 percent at 30 days to 24 percent at one year in the PARTNER 3 CT substudy. Planning a redo procedure is another, where CT establishes coronary occlusion risk and the root anatomy that determines sizing.


That last one deserves attention at the index case, not after it. CT simulation in patients modeled for TAVR-in-TAVR found coronary access technically impossible in 27 percent after a supra-annular index valve against 10 percent after an intra-annular one, with unimpeded access in 8 percent against 33 percent. The study is small and device-generation-specific, but the principle holds: the valve you choose today shapes what is possible in five years.


cvi42 reads all of it in one environment. The planning CT, the diagnostic cardiac CT, the CMR, and the follow-up study when a clinical question warrants one, against the same prior data, with no export and no second application.


The plan is the product


The procedure is a few hours. The plan is what determines how those hours go, and it is built somewhere else, by someone else, in software the operator usually does not touch.


Making that plan reproducible is not a workflow improvement. It is the difference between a measurement you accept and a measurement you would defend.


See how a structural heart case is planned in cvi42 →

By Jonathan Draper • August 13, 2026
Part 5 of 5 in Circle's Coronary Plaque series. Also read: Part 1 — How Advanced Plaque Analysis Changes the Clinic al Calculus Part 2 — Th e IT Infrastructure Behind CCTA Plaque Analysis Part 3 — The Financial Case for Coronary Plaque Services Part 4 — D elivering Plaque Analysis Without Disrupting Your Department You have watched the trajectory. Twelve months ago, the conversation about coronary plaque analysis was happening at conferences. Six months ago, it was happening in your referring cardiologists' offices. Now it is happening in your reading room — which lesions are vulnerable, what the total plaque burden is, whether coronary plaque tells a different story than the stenosis grade. That part is good news. Your patients are getting better assessments and the evidence base is catching up to the clinical intuition. On January 1, 2026, the financial case caught up too: the AMA retired the Category III plaque codes (0623T–0626T) and replaced them with a single Category I code, CPT 75577 , for AI-enabled coronary plaque assessment ( ACC Coding Corner ). Plaque analysis is no longer an emerging-technology line item. It is a national fee-schedule procedure. The harder question is operational: is your program set up to deliver it on its own — or to send the studies out and watch most of the reimbursement leave with them? For programs already running CCTA at any meaningful scale, becoming your own plaque lab is more accessible than most assume. It is a workflow choice, not a capital project.
Four people in a modern office meeting around a desk with multiple computer monitors.
June 25, 2026
Part 4 of 5 in Circle's Coronary Plaque series. Also read: Part 1 — How Advanced Plaque Analysis Changes the Clinical Calculus Part 2 — The IT Infrastructure Behind CCTA Plaque Analysis Part 3 — The Financial Case for Coronary Plaque Services It's Monday morning review. Throughput is off target again. Two radiologists are working through a backlog of CCTA studies from Friday. Your most experienced cardiac CT tech just submitted a PTO request for a week in July that you can't cover without asking someone else to come in. And now cardiology has sent a note asking why the plaque analysis reports are taking so long. This scenario is not unique to your department. It is the operational reality facing most cardiac imaging programs as CCTA volume grows and clinical expectations evolve faster than workflows do. Coronary plaque analysis has moved from a research capability to a clinical standard — driven by updated ACC/AHA Chest Pain Guidelines , 10-year SCOT-HEART outcomes and the ongoing SCOT-HEART 2 trial , and a growing population of patients and referring physicians who know what to ask for. Meeting that expectation with a manual workflow built for a simpler era of CCTA reporting is not a sustainable operating model. The question is not whether to offer plaque analysis. The question is how to build the workflow to deliver it without adding to a backlog that's already under pressure.

Person in green examines a glowing green sphere beside a white control panel in a green-toned room.
June 16, 2026
Part 3 of 5 in Circle's Coronary Plaque series. Also read: Part 1 — How Advanced Plaque Analysis Changes the Clinical Calculus Part 2 — The IT Infrastructure Behind CCTA Plaque Analysis The cardiology service line is under familiar financial pressure: rising volumes, tighter margins, growing competition from outpatient and independent imaging centers, and a capital environment that demands every major investment justify itself with a clear return. Against that backdrop, coronary plaque analysis has emerged as a meaningful financial opportunity — one with a growing reimbursement pathway, expanding referral demand, and the kind of clinical differentiation that drives patient retention. But the financial case only materializes if the program is set up to deliver the service efficiently and at scale. This is not an investment in a research capability. It is an investment in a billable, guideline-supported clinical service with a documented and growing payer footprint.
June 9, 2026
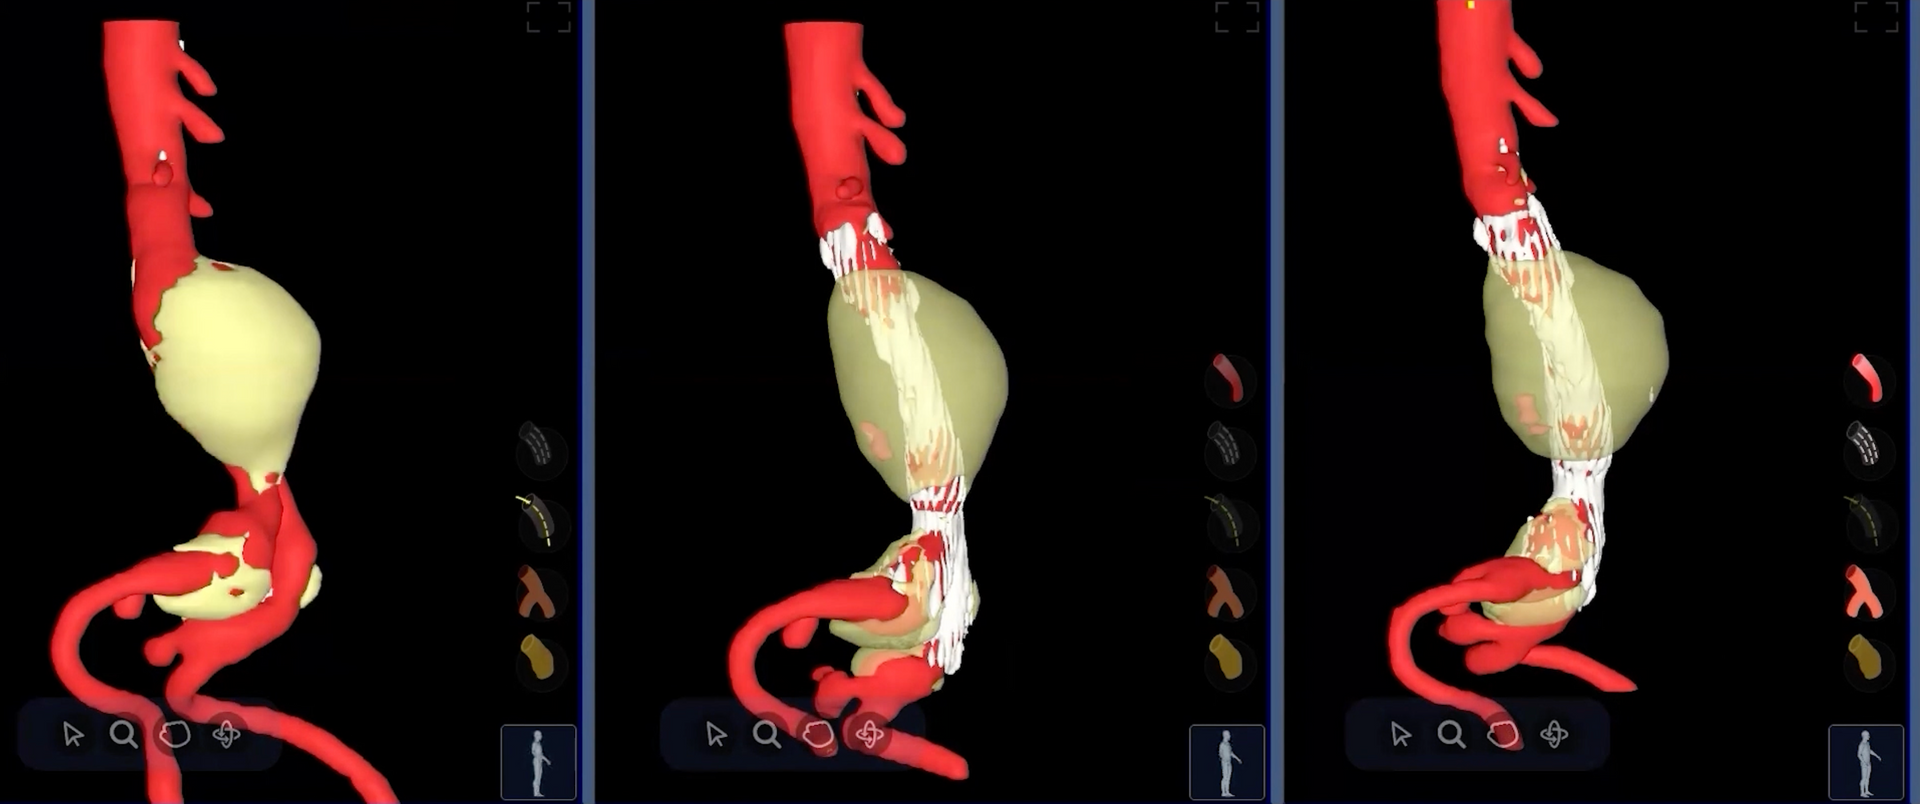
A landmark study shows that measuring how much an aneurysm sac shrinks in the first year after surgery can reliably forecast what that sac's diameter will do over the long haul — unlocking smarter, more personalised patient monitoring. The Problem with Watching Arteries Heal Abdominal aortic aneurysms — dangerous bulges in the body's main artery — kill tens of thousands of people each year when they rupture without warning. Endovascular aneurysm repair, or EVAR , is a minimally invasive surgery in which doctors thread a stent-graft through the groin to seal off the bulge from the inside, like patching a weak hose from within. It's revolutionised vascular surgery, offering patients a far quicker recovery than open surgery. But EVAR is not a cure. The sealed sac still exists inside the body, and over months and years it can change size — ideally shrinking as blood pressure is removed from it, but sometimes stubbornly staying the same or even growing. A sac that keeps expanding after surgery can signal a dangerous leak (called an endoleak ) or graft failure, either of which may require a second intervention. So, after every EVAR procedure, patients face a lifetime of periodic CT scans to check one simple thing: is the sac getting bigger or smaller? "For years, the number clinicians relied on was a single diameter measurement — essentially, how wide is the bulge? But width alone turns out to be a surprisingly blunt instrument." - Background context from the field of post-EVAR surveillance The challenge is that current guidelines require follow-up CT scans roughly every year for life, which is expensive, exposes patients to radiation, and still may miss subtle warning signs until they have become obvious on a simple diameter measurement. Researchers and clinicians have long wondered: is there a better, earlier signal we could use?

Subscribe to our newsletter

 Don’t miss future articles or publications.